Tag: texas abortion ban
Hope Negumezi with late wife Porsha and their sons

Devastated Dad Tells How Texas Abortion Ban Killed Young Mother Of His Boys

Texas dad Hope Negumezi shared with special correspondent Bonnie Fuller the tragic story of how his pregnant wife Porsha bled to death while waiting in agony for hours for medical care in Texas. Trigger warning for our readers: This story contains detailed descriptions of Porsha’s miscarriage and death in the hospital.

How the hell did my pregnant wife, Porsha, come to the hospital for help with a miscarriage and just a few hours later, leave in a body bag?

How was that possible?

That is what I couldn’t understand after my wife died suddenly in a Texas hospital while she hemorrhaged after a miscarriage. Why did this nightmare happen?

I learned later that same day in 2023 that her death was totally preventable. But I wouldn’t know for another year that my wife likely would be alive today if it hadn’t been for the Texas state Legislature and governor passing a law banning abortion.

Porsha and I were aware of the Texas abortion ban, which went into effect after Roe v. Wade was overturned by the US Supreme Court. But when she became pregnant with our third child, neither of us realized that it could affect the medical treatment of women having pregnancy complications.

Porsha was just 11 weeks pregnant with our third child and we were very excited. We had two young sons, 3 and 5, and wanted to have a large family, so we planned to keep on going.

It was June and the boys had just finished their school year. We decided to celebrate by taking a couple of days off and driving from our home in Houston to a water park called Kalahari, just outside of Austin.

Porsha had made all the arrangements for the vacation. She was always in charge of that. We had been married for six years but had been together since we met at Lamar University in Beaumont, Texas, in 2007.

Our first meeting was at my 21st birthday party. I had told my friends to bring some of their friends to the party and I spotted Porsha from across the room when she first walked in the door.

I had never met her before, but as soon as I saw her, it was like in the movies when everything stops. There seemed to be an aura around her. I went to the bathroom to splash water on my face to sober up and to figure out how I was going to talk to her.

I don’t know how it happened, but I was able to sit by her and we spoke for hours. It was so easy to talk to her. We just connected instantly.

I had never felt that with anyone else. I knew right away that she was “The One.” By January 2008, we were a couple and we had been together ever since.

When we got married, we had two weddings. One was an American white wedding. The other was a traditional Nigerian wedding. I was born here, but my parents both immigrated from Nigeria in the 1970s. Porsha’s family were all from Houston.

I’m an aircraft engineer and Porsha was a finance manager for a charter school in Houston.

She was a great mother. She just loved her boys so much and they loved her, too. They were both mama’s boys and were always hanging around her, which I loved.

She had no complications with those first two pregnancies or the births, even though she had a low platelet issue called chronic idiopathic thrombocytopenic purpura.

[Editor’s Note: Chronic idiopathic thrombocytopenic purpura can cause easy bleeding and difficulty clotting. Porsha also suffered from iron deficiency anemia and had sickle cell trait.]

Porsha’s OB-GYN at the time of her first two pregnancies was aware of her condition and was careful to monitor her.

We didn’t expect that we would have any complications with the third pregnancy. On the day that we left for Austin, though, Porsha noticed some spotting. She called her OB-GYN.

This was a new OB-GYN and Posha hadn’t met her yet. Her old OB-GYN had moved away. Porsha explained to her doctor what was happening. The doctor told her that if the spotting became more frequent, it could be a miscarriage and that she should go to a hospital emergency room.

We were at the water park for two days. On the day that we began the drive home, Porsha’s spotting was becoming heavier.

We were both getting worried. I remember that I reached over and grabbed her hand and she smiled at me. We decided that as soon as we arrived home, Porsha would head immediately to Houston Methodist Sugar Land Hospital.

It was about 10 minutes away in a suburb outside of Houston. It seemed like a very nice hospital and we thought we would get better care there than going downtown.

I would stay with the boys until my mother could get over to babysit and then I would join her.

By the time Porsha got to the hospital at 3:37 p.m., the bleeding had become heavy. After she had been there for about three hours, she went to the bathroom and had a partial miscarriage there. A lot of blood and blood clots came out.

She texted me while I was giving the boys a bath and we were both heartbroken. I learned later after she died that she had been pregnant with a daughter. We had both wanted a girl so much.

Nevertheless, I felt that Porsha was in good hands at the hospital. After all, women have miscarriages. It happens and doctors are trained to handle women with miscarriages. This wasn’t a unique situation.

Porsha was taken to get an ultrasound, which confirmed that she had lost the baby. There was no heartbeat.

But she had lost so much blood that the ER doctor ordered a blood transfusion for her. The nurse was about to give her a blood transfusion when I arrived.

We were talking. She said that she was cold and I was leaning over to hug her and warm her up when she started to slur her words and suddenly she lost consciousness.

It was really scary.

Luckily, the nurse caught the situation and she came rushing in and began administering the transfusion.

She told me to try and keep Porsha conscious. I was telling her, “Babe, stay with me. Stay with me.”

She regained consciousness but she still hadn’t seen a hospital OB-GYN—just the ER doctor—even though she’d been there for hours. She was still passing blood clots as big as grapefruits.

Porsha doesn’t like hospitals and the whole time she was there that afternoon and evening, she was worried and scared. I kept reassuring her, “It’s going to be over and we’ll get out of here and be back home with our kids.”

I was trying to keep her spirits up. We called my mom, who trained as a doctor in the Dominican Republic and had practiced there before she moved to the US. Since she’s been here, she’s worked as a clinical research associate, focusing on cancer research.

She was in Dallas because one of my two sisters—who are both nurses—had just given birth there.

My mother told us that Porsha needed a minor and common procedure called a D&C (dilation and curettage) in order to clean out her uterus by removing all the fetal tissue which remained in it after the partial miscarriage.

Editor’s Note: Without a D&C, the uterus may keep trying to expel material in it by contracting and bleeding.

It was after speaking to my mother that the hospital OB-GYN, Dr. Andrew Ryan Davis, finally showed up and did his medical evaluation. It sounded like he knew what he was talking about.

He said, “It is our routine to first have Porsha take the drug misoprostol and see if that helps to pass the remaining fetal matter and blood clots. If that doesn’t work, then we can do a D&C.”

[Editor’s Note: More than a dozen doctors who reviewed Porsha’s case for the news site ProPublica concluded that misoprostol can be an effective drug to end early, low-risk miscarriage, but was inappropriate for Negumezi, who had been bleeding heavily and suffered from a low platelet condition. The Texas Medical Board, which reviewed Porsha’s case, confirmed that she should have been given a D&C immediately because of the volume of blood she was losing.]

Even though what Dr. Davis said conflicted with my mom’s advice, Porsha and I trusted him. He was the staff OB-GYN and he said that this was the hospital’s routine procedure. We accepted that Porsha’s miscarriage was “routine” and he gave her the drug.

He also told us that he was going to move Porsha out of the ER and to a section of the hospital where he could reach her more quickly. But the ER nurse who had been taking care of Porsha came to talk with us and she said, “If you don’t feel right about the move, then say something.”

Even though I wasn’t sure that leaving the ER was the right move, we again decided to follow the doctor’s advice. But on the way up to the room, Porsha said that her chest was hurting.

Her new nurse treated her complaint like it was something normal and brought her Tylenol. However, over the next couple of hours, Porsha complained another four times that her chest hurt.

I began to get more and more upset because no one was doing anything. The doctor didn’t come to check on her and finally, after Porsha complained a fifth time, the nurse brought her morphine for the pain.

Editor’s Note: Chest pain in Porsha’s condition was caused by her heart not receiving enough oxygen from her blood due to her severe blood loss, according to a consultation with a Texas OB-GYN, who read about Porsha’s case.

Porsha was also incredibly thirsty because she wasn’t supposed to drink since the misoprostol hadn’t fully dissolved on her tongue.

I remember that we were having a conversation about how she couldn’t wait to get out of the hospital to see the boys and get something to eat when she just started gasping for air.

I grabbed the hospital telephone and screamed to the nurse, “Something’s wrong with my wife, she can’t breathe!” It was about 1:30 A.M.

I remember that the nurse came in and she began calling “Code Blue” or something like that.

More people came into her room, but there didn’t seem to be any sense of urgency like on TV shows about medical emergencies when everyone’s rushing to try to save someone’s life.

I was pushed aside but I was telling Porsha, “Come on babe, you’re going to be alright. Come on, Babe. This is not going to be our ending. You’re going to make it.”

The medical team injected her with something, they were doing CPR and they gave her heart electric shocks several times from defibrillator paddles.

I was crying, I was shouting, I was praying. I felt like I was having an out-of-body experience.

There was a female doctor and she pulled me out of the room and told me to call Porsha’s mom, which I did.

Her mother must have heard the panic in my voice. I told her that she needed to get to the hospital now. She lived close by and she and Porsha’s stepdad got there really quickly.

The ER doctor that had seen Porsha earlier arrived and I could hear him say, “Let’s do this and then that" but there was no urgency in his voice. I went back into Porsha’s room and I heard him say, “Anybody have any ideas?”

I was like, what?

Then he told me, “We’re not seeing or hearing any heartbeat.”

It felt to me like he was trying to get my OK for them to stop trying to revive her. But I said, “You got to do more. You got to try.” I just could not accept that he was trying to tell me that Porsha had died.

The OB-GYN finally showed up and that’s when the staff announced that Porsha was deceased. It was 2 a.m. Porsha had arrived there at about 3:30 p.m. in the afternoon. It had been about 10 hours since she had first walked into the hospital alive and in need of help for a miscarriage.

Despite the medical team announcing that she had died, I kept thinking that Porsha would come back. I wanted her to wake up so bad. I took her hand and it was cold but I felt like I could warm her up. Porsha always called me “the heater.”

She used to get cold really quickly and would come to me to just warm her. But now, she stayed cold.

Her mom had gotten in the bed with her and was crying.

I didn’t leave the hospital until the sun was coming up. I waited until the coroner came to get her body to do an autopsy. I walked with her as he rolled her away. Her cause of death was vaginal hemorrhage.

Then I just jumped in my car and left.

I was scared of what would happen to me. I felt so broken. I wasn’t myself and I didn’t want my sons to see how upset I was. I was thinking that I wanted to get them dressed and dropped off at their summer camp so I could get my state of mind back while they had a normal day.

I was fighting back tears as I got them dressed and they kept asking, “Where’s mommy?” I told them that she was still at the hospital.

The moment that I got them into their camp, which was at the local school, I broke down. The principal and the assistant principal came out and I told them what happened.

The pain damn near killed me. It hurt so much.

I realized that Porsha’s death was preventable later that day. A lot of my mom’s friends who are in the medical field came by my house and they all said that she should have been given a D&C, not the misoprostol. They kept repeating, “All they had to do was clean her uterus out.”

One of the guys said, “She already had the miscarriage. It wasn’t an abortion. Why couldn’t they give her a D&C?”

It made me so angry but also made me feel so terrible. How could I not have known that?

I kept going over everything that had happened in my head to figure out what I did wrong. I felt shame. Porsha had needed the emergency D&C.

When I looked back at those hours in the hospital, I felt like there had been so many times that the OB-GYN could have intervened to save her life. But he never came back to see her until after she died.

I didn’t tell my sons that their mommy had died for a couple more days. I didn’t know how to do it. I just remember crying a lot when I finally broke the news to them. What hurt the most was the confused look on their faces.

My older son, who was just five, was trying to understand. But a couple of days later, they were both asking again, “Where’s Mommy?”

When my youngest son, who was three, would see a woman with braids like his mom had been wearing, he would just take off and run to her thinking that was his mom.

Still today, three years later, they say, “I miss Mommy.” They remember her. They remember the trip to the water park.

One of my fears has been letting depression check me out. My sons already lost their mother, so I have to be available to them. I’ve had to summon all my strength to get up every day despite having low energy.

I have to put a smile on my face, wake the boys up and start their morning off great. The single dad thing has been tough, especially as I’ve coped with the grief.

But luckily their grandmothers and aunties live close by and I can take them to them to get lots of hugs and cuddles and extra love.

I didn’t realize that Texas’s abortion ban could be a contributor to Porsha’s death until I was contacted by reporters from the ProPublica news organization, who were researching Porsha’s medical situation for a story, about a year after she died.

Porsha had been upset when Roe v. Wade was overturned. She didn’t like seeing rights taken away from women.

But neither of us thought the Texas abortion ban could ever play a role in her pregnancy or that the treatment she received while miscarrying was being affected by the law.

But once I spoke with the ProPublica journalists, I realized that it creates a lot of gray areas which prevent doctors from doing what they need to do to care for women having pregnancy complications.

On top of that, the punishment for doctors performing an abortion is so great that it could affect their medical decisions.

[Editor’s Note: Doctors in Texas face up to 99 years in prison for performing an abortion that is deemed medically unnecessary, in addition to the loss of their medical license.]

Connecting those dots and relating them to Porsha and how her care was put in jeopardy was just sickening to me.

My belief had always been that laws are here to protect us and make life better for us. Not kill us.

Bonnie Fuller is the former CEO and editor-in-chief of HollywoodLife.com and former editor-in-chief of Glamour, Cosmopolitan, Marie Claire, and USWeekly. Follow her substack, Bonnie Fuller: Your Body Your Choice. from which this is reprinted with permission.

Reprinted with permission from Courier Texas

In Her Own Words: Why This Doctor Fled Texas To Help Women In Virginia

In Her Own Words: Why This Doctor Fled Texas To Help Women In Virginia

Dr. Lou Rubino is just one of many physicians who’ve left Texas as a result of the state’s multiple abortion bans—laws that prevent doctors from treating pregnant women with not just abortion care, but life-saving emergency care. She’s now practicing in Virginia.

Dr. Rubino told her story to writer Bonnie Fuller for Dogwood.

I remember very clearly the moment I knew I was done. I could no longer practice as a women’s health care doctor in Texas.

I had a patient, probably 18 or 19 years old. I was doing an ultrasound, and she told me she needed an abortion for her safety. She said, “I’m too young. I don’t feel safe with my partner. I’m scared. I need an abortion.”

When a patient tells me they feel unsafe with a partner, I take that very seriously. Pregnant people are at high risk of harm from abusive partners. It’s a dangerous time. She knew what she needed, and I knew it was wrong for me to say no.

She was very early in her pregnancy, between six and eight weeks. I should have been able to prescribe abortion pills or perform a quick five-minute procedure. Instead, I had to tell her she could not get care in Texas. I explained she’d have to travel nearly nine hours to the nearest clinic.

She cried, and I cried. I told her this was wrong, that her rights were being violated, and that I couldn’t let her believe she was the one at fault. After that, I knew I couldn’t go on. I put down my things, walked out, and decided to leave Texas for good.

I asked myself: Am I the kind of doctor who does the wrong thing?
I’m not. And Texas couldn’t force me to be.

Not long after, my husband and I moved to Virginia, where I now practice.

‘I moved to Austin for something different’

I’m originally from Detroit and went to medical school at Southern Illinois University. I moved to Austin in 2015 for something different, met my husband, and did my residency at UT Southwestern in Dallas.

At first, I didn’t think of abortion as a political issue. But quickly, I realized that without abortion and miscarriage training, I’d be ignoring an essential part of women’s health.

Miscarriages are common—about 15 percent of pregnancies end that way. Abortions are also common—one in four women will have one. To ignore that would mean I wasn’t fully trained.

In Texas, there was no formal abortion training. Instead, I apprenticed with an OB-GYN in Austin and learned to perform medication abortions and procedures up to 18 weeks. I became the main doctor at the Austin Women’s Health Center for several years, and I loved it. Providing a safe abortion can completely change someone’s life.

Then came the bans. After Senate Bill 8 passed in 2021, prohibiting abortions after six weeks, I began making plans to leave. I didn’t want to abandon my patients, but I also knew the state was stripping me of my job and my oath as a physician. When the Supreme Court overturned Roe v. Wade in 2022, Texas’s trigger ban outlawed abortion from conception.

I realized I couldn’t protect my staff while breaking the law. The day I had to turn away that young patient made me understand: By following the law, I was doing the wrong thing medically. I walked out of the clinic for good.

‘We get anti-abortion patients coming in for abortions, too’

I took work in Virginia and eventually helped open Meadow Reproductive Health and Wellness Clinic in McLean, just outside Washington, D.C. I’m now its medical director. We provide abortions up to 15 weeks and hope to expand to 18 when we grow our staff. About 20 percent of our patients come from out of state—often driving through the night from places like Florida, Georgia, or Alabama. Some bring children because they don’t have childcare. We started stocking microwaveable meals because a lot of people can’t afford food while traveling.

Every out-of-state patient has a story of desperation—needing time to gather money, arrange childcare, or escape an abusive partner. Too many people who need abortions aren’t getting them at all.

Now, in Virginia, I can practice the way I was trained. I no longer have to wonder whether my medical advice could land me in court. In Texas, at one point, I even asked myself, “Am I supposed to follow state laws or a tweet from the attorney general?”

I understand at a really fundamental level that the most basic human right is bodily autonomy. Without the right to control your pregnancy, you don’t have it. And without good reproductive health care, you risk your quality of life—or your life itself.

We get “anti-abortion” and deeply religious people coming in for abortions, too. They come to us for the same reasons anyone does: financial hardship, health risks, education, safety. They’re human, too.

I was nervous to tell my conservative grandmother in Tennessee about my work. But when I did, she surprised me. She said: “If someone needs an abortion, I’d want you to be the one doing it. I’m glad you’re doing that.”

Leaving Texas has been a relief. Here in Virginia, I can focus on patients and provide care in the right ways—medically, safely. You see, I took an oath as a doctor and I take it very seriously.

From the editor: How abortion bans are impacting Virginia and its neighbors

Abortion bans in Southern states have compelled expert doctors like Dr. Lou Rubino to relocate to Virginia, where laws allow medical professionals to provide essential reproductive health care. Clinics such as Meadow Reproductive Health and Wellness now serve not only Virginians, but also a growing number of women traveling from states where access is restricted—including Texas. These patients often arrive after long and difficult journeys, seeking safe and legal abortion care that is increasingly unavailable closer to home.

Reprinted with permission from VaDogwood.

Texas Abortion Law Would Have Forced Me To Watch My Baby Die

Texas Abortion Law Would Have Forced Me To Watch My Baby Die

Eighth-generation Texan Megan Bond recounted the stories of her dangerous pregnancies to COURIER Texas writer Bonnie Fuller. Here’s what happened, in her own words:

I feel bad for anyone who was in the medical office at the time I and my husband learned that our second desperately wanted baby was suffering from the same fatal fetal anomaly, bilateral renal agenesis, as our first baby.

This wasn’t supposed to happen. We had been told that there was only a one percent chance that we could have a second baby with bilateral renal agenesis, a condition in which your baby develops with no kidneys and no lungs so it will suffocate just after birth.

I was 15 weeks pregnant and had just had my anatomy scan. As my husband, Kevin, and I watched the technician, we could see for ourselves on the ultrasound screen that our baby boy, Teddy, had no amniotic fluid around him inside my womb.

We knew that meant that he had no kidneys, like our first baby, Keith, who we had made the very difficult decision to abort, because he was going to die right after birth.

We had learned through this first heartbreaking experience that kidneys are necessary to produce a fetus’s amniotic fluid. Without amniotic fluid, it’s impossible for a baby’s lungs to develop.

Even though we had now seen that Teddy’s little body was not surrounded by amniotic fluid, we were hoping against hope that we were wrong, as we waited in utter silence for the maternal fetal medicine specialist to come in and see us.

Every second waiting was agony.

Then she came in and confirmed the worst possible news—our second precious baby wouldn’t survive.

Time just stood still. My scream was irrepressible. Emotions just took over.

My husband and I hadn’t even told our parents that I was pregnant. But now we couldn’t put it off. We had to call and tell them the news immediately—both that I was pregnant, and that I was losing this new much longed-for baby.

I had first met Kevin when I was 30. We were married in October of 2022 and by the fall of 2023, after trying to conceive, we learned that we would have to go through IVF (in vitro fertilization) in order to have a family.

Happily, we were able to make seven embryos and when we transferred our first embryo it took, which was fantastic.

We found out that we were going to have a little boy as our first child, and I knew that I wanted to name him Keith after my paternal grandfather.

That was one of the best moments of my life—when I told my dad and he cried, knowing that his dad’s name was going to live on.

We got the happy news about my pregnancy two days before Christmas, so we were able to tell everybody during our Christmas celebrations that we were pregnant. Can you imagine a better gift than telling your parents that they would be grandparents?

And oh my gosh, everybody cried.

Not surprisingly, when we were at our first anatomy scan at 17 weeks, Kevin and I were very excited. We were watching our baby move around and we were looking at his heartbeat. We didn’t know that anything was wrong until our maternal fetal medicine specialist came in and told us.

She explained that our son had no kidneys, which meant that there was no amniotic fluid around him, and with no amniotic fluid his lungs couldn’t develop.

This meant that he would be crushed in utero without the amniotic fluid, and then if he did survive until birth he would suffocate because his lungs wouldn’t work, and it would be incredibly painful for him.

I knew immediately that the decision I would make was to terminate the pregnancy with an abortion. I could take on my baby’s pain so he wouldn’t have to do it.

Later, we talked to other doctors about our son’s condition but every one of them said the same thing: No baby with this diagnosis had ever survived.

Learning about our options

Before this happened to us, I was only vaguely aware of the abortion laws in Texas. I just knew that the law was terrible and that you couldn’t get an abortion in Texas.

What happened after the maternal fetal medicine specialist told us about the fatal diagnosis for Keith is all kind of a blur.

I do know that I immediately asked: “What can we do about this?” And her answer was, “Nothing.”

I also asked if, in our case with this diagnosis, I could end the pregnancy in Texas and she said, “No, in Texas your only option is to carry to term.”

Then I asked if it was legal somewhere else. I could tell that she was very hesitant to respond, but she did say yes.

I realize that she stopped talking because she was afraid and I don’t blame her. I don’t hold any grudges because there is so much at stake for doctors.

My husband and I were in complete shock after we found this out. We had had a healthy pregnancy. I had counted down the weeks of the first trimester knowing that’s when most of the miscarriages happen.

The invitations to a baby shower that my best friend was going to hold had already gone out two days before. We actually received it in the mail two days after we got the deadly diagnosis for Keith.

When Kevin and I got to the parking lot after the anatomy scan, we just bawled in each other’s arms.

Then we told our parents. I don’t know how Kevin drove home.

I was not mentally able to do the research to figure out what to do. Luckily, my dad’s a retired physician so he knew what to look for. He found us a clinic in Denver that could get us in before I reached their 20-week cutoff.

My parents, despite learning that their only grandbaby wasn’t going to survive, were there to support us, find us all comfortable places to stay, and come with us to the clinic.

We really were lucky despite the terrible situation, because we had full support from both sides of our family. No one was questioning our decision. No one was making us feel guilty, which is not the situation for a lot of women.

At the clinic in Denver…and after

The staff at the clinic were all so kind and knowledgeable. They said all the right things.

It was a two-day procedure and they let my husband be there as much as possible, including during the termination procedure, which I’m sure was incredibly difficult for him.

At first it was too overwhelming for Kevin and me to think about trying to get pregnant again. But about three months later, we decided to try with another of the embryos we had made during our IVF treatment.

We were told by all the doctors that we consulted that having another baby with bilateral renal agenesis would be like having lightning strike twice.

We had six embryos left, and our IVF doctors told us they were excited for us to try again. That we were going to be parents.

I got pregnant right away again, but we were so nervous we didn’t tell our parents this time. After what we had just been through with Keith and the abortion, we were really robbed of the joy of pregnancy. The joy of being optimistic.

We couldn’t plan a nursery. The first time I got pregnant, my husband went out and bought a ton of maternity clothes for me because he was so excited. But this time, neither of us did anything to prepare.

After we got the devastating news that I was losing a second baby to the same fatal fetal anomaly, we decided that we had to get the best genetic expert counseling that we could.

My IVF doctor recommended that we consult with Dr. Mark Evans in New York City. We wanted to see him before undergoing the second abortion, so we could do an amniocentesis procedure and get full genome testing.

We were desperate to learn why this had happened to us twice, especially when it was such a rare condition and we had no history of kidney issues in our families.

He spent four hours with us and was so empathetic. He explained everything that he was doing and answered all our questions but all the tests he did turned up nothing that could have caused the bilateral renal agenesis in our babies.

Unfortunately, there is nothing we can look at or test for in future pregnancies to prevent it.

We had to fly from New York City back to Colorado for a second procedure, where my parents met us again to provide support. I don’t even remember how we got back to Texas—it’s such a blur.

‘I think Texas’s abortion bans are cruel’

I think Texas’s abortion bans are cruel. The decision to have an abortion should be between a mother, whoever she wants to consult, and her very qualified team of professionals who spend years studying.

I think people should have autonomy to make their own decisions.

I don’t think politicians, with no medical experience, should be making decisions about abortion. They aren’t even listening to what doctors are saying.

Essentially I believe in smaller government. But this is big government. This is government getting involved in people’s personal lives and making decisions for them.

One of the first reactions I had to the news that the Texas law would force me to carry a doomed baby to birth was: “How do I sue the state?” No one should have to leave their state to get medical care to terminate a pregnancy.

We were very fortunate. We found a good clinic to go to. We had flexible jobs so we could take time off. In fact, I’m the CEO of a small business. We also had parental support and we could afford to do all of this. It probably cost us $10,000.

But how many people have $10,000 sitting around?

I don’t want people who aren’t in our situation to have to carry a baby to term and not have a choice. We had the choice available to us to leave Texas, but very few people do.

My goal is to get Republican lawmakers who control the Texas legislature to add an exception to the abortion bans for lethal fetal anomalies. That’s not saying that fighting the laws should stop there, but I am wary about how much I and other advocates will be able to do in this state. But this is what I can do in my situation.

When I tell my story, people are convinced. They don’t believe that women should have to carry a baby that has a fatal fetal anomaly and will die right after birth, like Keith and Teddy would have.

They agree that an abortion under this circumstance should not be illegal. Even my most right wing friends or people that I talk to who are “pro life” think there should be an exception to the abortion law for fatal fetal anomalies.

I know it’s going to be very hard to get things to change in Texas. People aren’t educated on the issues and people just go and vote Red all the way down the line.

After Keith died I wrote to every single politician in the state whose email address I could find. I also wrote to the members of the state Supreme Court.

However, the only response I got was a form letter from one legislator telling me that they were “doing all we could to protect unborn children.”

My letters had fallen on deaf ears.

I’m an eighth-generation Texan. I love my state, but my state doesn’t love me.

But I will still keep educating people. And now I have people advocating for me. They know my story and whenever they hear someone saying that stories about women being forced to carry babies that will die right after birth are fake, they explain to them that they are wrong and that this happened to Megan.

Despite everything we have been through, my husband and I still want to have a family, so we want to try again.

It’s a heavy decision to make knowing what potential pain we’re putting ourselves into. We really hope to have a family some day in the future—but we are more fearful every day about the fact that it is getting more and more difficult to safely have a family.

Bonnie Fuller is the former CEO and editor-in-chief of HollywoodLife.com and former editor-in-chief of Glamour, Cosmopolitan, Marie Claire, and USWeekly.

Reprinted with permission from Courier Texas.

Texas Banned Abortion -- Then Deadly Sepsis Among Pregnant Women Soared

Texas Banned Abortion -- Then Deadly Sepsis Among Pregnant Women Soared

Reprinted with permission from ProPublica

By Lizzie Presser, Andrea Suozzo, Sophie Chou and Kavitha Surana

Pregnancy became far more dangerous in Texas after the state banned abortion in 2021, ProPublica found in a first-of-its-kind data analysis.

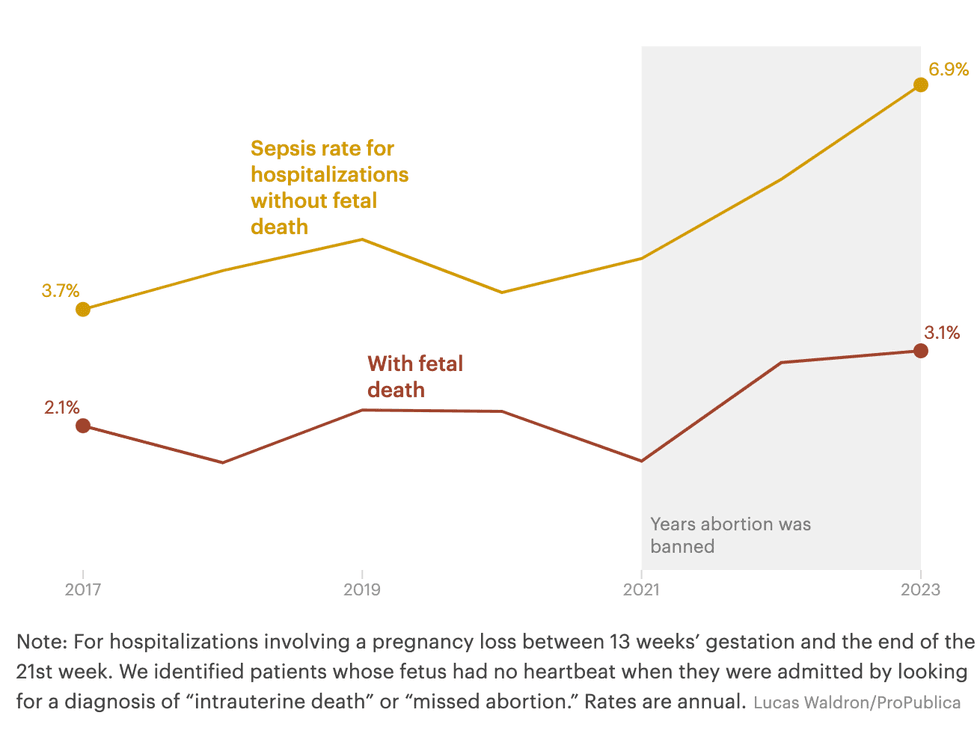
The rate of sepsis shot up more than 50 percent for women hospitalized when they lost their pregnancies in the second trimester, ProPublica found.

The surge in this life-threatening condition, caused by infection, was most pronounced for patients whose fetus may still have had a heartbeat when they arrived at the hospital.

ProPublica previously reported on two such cases in which miscarrying women in Texas died of sepsis after doctors delayed evacuating their uteruses. Doing so would have been considered an abortion.

The new reporting shows that, after the state banned abortion, dozens more pregnant and postpartum women died in Texas hospitals than had in pre-pandemic years, which ProPublica used as a baseline to avoid COVID-19-related distortions. As the maternal mortality rate dropped nationally, ProPublica found, it rose substantially in Texas.

ProPublica’s analysis is the most detailed look yet at a rise in life-threatening complications for women losing a pregnancy after Texas banned abortion. It raises concerns that the same pattern may be occurring in more than a dozen other states with similar bans.

To chart the scope of pregnancy-related infections, ProPublica purchased and analyzed seven years of Texas’ hospital discharge data.

When abortion was legal in Texas, the rate of sepsis for women hospitalized during second-trimester pregnancy loss was relatively steady. Then the state’s first abortion ban went into effect and the rate of sepsis spiked.


Chart via Pro Publica

“This is exactly what we predicted would happen and exactly what we were afraid would happen,” said Dr. Lorie Harper, a maternal-fetal medicine specialist in Austin.

She and a dozen other maternal health experts who reviewed ProPublica’s findings say they add to the evidence that the state’s abortion ban is leading to dangerous delays in care. Texas law threatens up to 99 years in prison for providing an abortion. Though the ban includes an exception for a “medical emergency,” the definition of what constitutes an emergency has been subject to confusion and debate.

Many said the ban is the only explanation they could see for the sudden jump in sepsis cases.

The new analysis comes as Texas legislators consider amending the abortion ban in the wake of ProPublica’s previous reporting, and as doctors, federal lawmakers and the state’s largest newspaper have urged Texas officials to review pregnancy-related deaths from the first full years after the ban was enacted; the state maternal mortality review committee has, thus far, opted not to examine the death data for 2022 and 2023.

The standard of care for miscarrying patients in the second trimester is to offer to empty the uterus, according to leading medical organizations, which can lower the risk of contracting an infection and developing sepsis. If a patient’s water breaks or her cervix opens, that risk rises with every passing hour.

Sepsis can lead to permanent kidney failure, brain damage and dangerous blood clotting. Nationally, it is one of the leading causes of deaths in hospitals.

While some Texas doctors have told ProPublica they regularly offer to empty the uterus in these cases, others say their hospitals don’t allow them to do so until the fetal heartbeat stops or they can document a life-threatening complication.

Last year, ProPublica reported on the repercussions of these kinds of delays.

Forced to wait 40 hours as her dying fetus pressed against her cervix, Josseli Barnica risked a dangerous infection. Doctors didn’t induce labor until her fetus no longer had a heartbeat.

Physicians waited, too, as Nevaeh Crain’s organs failed. Before rushing the pregnant teenager to the operating room, they ran an extra test to confirm her fetus had expired.

Both women had hoped to carry their pregnancies to term, both suffered miscarriages and both died.

In response to their stories, 111 doctors wrote a letter to the Legislature saying the abortion ban kept them from providing lifesaving care and demanding a change.

“It’s black and white in the law, but it’s very vague when you’re in the moment,” said Dr. Tony Ogburn, an OB-GYN in San Antonio. When the fetus has a heartbeat, doctors can’t simply follow the usual evidence-based guidelines, he said. Instead, there is a legal obligation to assess whether a woman’s condition is dire enough to merit an abortion under a prosecutor’s interpretation of the law.

Some prominent Texas Republicans who helped write and pass Texas’ strict abortion bans have recently said that the law should be changed to protect women’s lives — though it’s unclear if proposed amendments will receive a public hearing during the current legislative session.

ProPublica’s findings indicate that the law is getting in the way of providing abortions that can protect against life-threatening infections, said Dr. Sarah Prager, a professor of obstetrics and gynecology at the University of Washington.

“We have the ability to intervene before these patients get sick,” she said. “This is evidence that we aren’t doing that.”

A New View

Health experts, specially equipped to study maternal deaths, sit on federal agencies and state-appointed review panels. But, as ProPublica previously reported, none of these bodies have systematically assessed the consequences of abortion bans.

So ProPublica set out to do so, first by investigating preventable deaths, and now by using data to take a broader view, looking at what happened in Texas hospitals after the state banned abortion, in particular as women faced miscarriages.

“It is kind of mindblowing that even before the bans researchers barely looked into complications of pregnancy loss in hospitals,” said perinatal epidemiologist Alison Gemmill, an expert on miscarriage at Johns Hopkins Bloomberg School of Public Health.

In consultation with Gemmill and more than a dozen other maternal health researchers and obstetricians, ProPublica built a framework for analyzing Texas hospital discharge data from 2017 to 2023, the most recent full year available. This billing data, kept by hospitals and collected by the state, catalogues what happens in every hospitalization. It is anonymized but remarkable in its granularity, including details such as gestational age, complications and procedures.

To study infections during pregnancy loss, ProPublica identified all hospitalizations that included miscarriages, terminations and births from the beginning of the second trimester up to 22 weeks’ gestation, before fetal viability. Since first-trimester miscarriage is often managed in an outpatient setting, ProPublica did not include those cases in this analysis.

When looking at stays for second-trimester pregnancy loss, ProPublica found a relatively steady rate of sepsis before Texas made abortion a crime. In late 2021, the state made it a civil offense to end a pregnancy after a fetus developed cardiac activity, and in the summer of 2022, the state made it a felony to terminate any pregnancy, with few exceptions.

In 2021, 67 patients who lost a pregnancy in the second trimester were diagnosed with sepsis — as in the previous years, they accounted for about three percent of the hospitalizations.

In 2022, that number jumped to 90.

The following year, it climbed to 99.

ProPublica’s analysis was conservative and likely missed some cases. It doesn’t capture what happened to miscarrying patients who were turned away from emergency rooms or those like Barnica who were made to wait, then discharged home before they returned with sepsis.

Our analysis showed that patients who were admitted while their fetus was still believed to have a heartbeat were far more likely to develop sepsis.

“What this says to me is that once a fetal death is diagnosed, doctors can appropriately take care of someone to prevent sepsis, but if the fetus still has a heartbeat, then they aren’t able to act and the risk for maternal sepsis goes way up,” said Dr. Kristina Adams Waldorf, professor of obstetrics and gynecology at UW Medicine and an expert in pregnancy complications. “This is needlessly putting a woman’s life in danger.”

Studies indicate that waiting to evacuate the uterus increases rates of sepsis for patients whose water breaks before the fetus can survive outside the womb, a condition called previable premature rupture of membranes or PPROM. Because of the risk of infection, major medical organizations like the Society for Maternal-Fetal Medicine and the American College of Obstetricians and Gynecologists advise doctors to always offer abortions.

Researchers in Dallas and Houston examined cases of previable pregnancy complications at their local hospitals after the state ban. Both studies found that when women weren’t able to end their pregnancies right away, they were significantly more likely to develop dangerous conditions than before the ban. The study of the University of Texas Health Science Center in Houston, not yet published, found that the rate of sepsis tripled after the ban.

Dr. Emily Fahl, a co-author of that study, recently urged professional societies and state medical boards to “explicitly clarify” that doctors need to recommend evacuating the uterus for patients with a PPROM diagnosis, even with no sign of infection, according to MedPage Today.

UTHealth Houston did not respond to several requests for comment.

ProPublica zoomed out beyond the second trimester to look at deaths of all women hospitalized in Texas while pregnant or up to six weeks postpartum. Deaths peaked amid the COVID-19 pandemic, and most patients who died then were diagnosed with the virus. But looking at the two years before the pandemic, 2018 and 2019, and the two most recent years of data, 2022 and 2023, there is a clear shift:

In the two earlier years, there were 79 maternal hospital deaths.

In the two most recent, there were 120.

Caitlin Myers, an economist at Middlebury College, said it’s crucial to examine these deaths from different angles, as ProPublica has done. Data analyses help illuminate trends but can’t reveal a patient’s history or wishes, as a detailed medical chart might. Diving deep into individual cases can reveal the timeline of treatment and how doctors behave. “When you see them together, it tells a really compelling story that people are dying as a result of the abortion restrictions.”

Texas has no plans to scrutinize those deaths. The chair of the maternal mortality review committee said the group is skipping data from 2022 and 2023 and picking up its analysis with 2024 to get a more “contemporary” view of deaths. She added that the decision had “absolutely no nefarious intent.”

“The fact that Texas is not reviewing those years does a disservice to the 120 individuals you identified who died inpatient and were pregnant,” said Dr. Jonas Swartz, an assistant professor of obstetrics and gynecology at Duke University. “And that is an underestimation of the number of people who died.”

The committee is also prohibited by law from reviewing cases that include an abortion medication or procedure, which can also be used during miscarriages. In response to ProPublica’s reporting, a Democratic state representative filed a bill to overturn that prohibition and order those cases to be examined.

Because not all maternal deaths take place in hospitals and the Texas hospital data did not include cause of death, ProPublica also looked at data compiled from death certificates by the Centers for Disease Control and Prevention.

It shows that the rate of maternal deaths in Texas rose 33% between 2019 and 2023 even as the national rate fell by 7.5%.

A New Imperative

Texas’ abortion law is under review this legislative session. Even the party that championed it and the senator who authored it say they would consider a change.

On a local television program last month, Republican Lt. Gov. Dan Patrick said the law should be amended.

“I do think we need to clarify any language,” Patrick said, “so that doctors are not in fear of being penalized if they think the life of the mother is at risk.”

State Sen. Bryan Hughes, a Republican who once argued that the abortion ban he wrote was “plenty clear,” has since reversed course, saying he is working to propose language to amend the ban. Texas Gov. Greg Abbott told ProPublica, through a spokesperson, that he would “look forward to seeing any clarifying language in any proposed legislation from the Legislature.”

Patrick, Hughes and Attorney General Ken Paxton did not respond to ProPublica’s questions about what changes they would like to see made this session and did not comment on findings ProPublica shared.

In response to ProPublica’s analysis, Abbott’s office said in a statement that Texas law is clear and pointed to Texas health department data that shows 135 abortions have been performed since Roe was overturned without resulting in prosecution. The vast majority of the abortions were categorized as responses to an emergency but the data did not specify what kind. Only five were solely to “preserve [the] health of [the] woman.”

At least seven bills related to repealing or creating new exceptions to the abortion laws have been introduced in Texas.

Doctors told ProPublica they would most like to see the bans overturned so all patients could receive standard care, including the option to terminate pregnancies for health considerations, regardless of whether it’s an emergency. No list of exceptions can encompass every situation and risk a patient might face, obstetricians said.

“A list of exceptions is always going to exclude people,” said Dallas OB-GYN Dr. Allison Gilbert.

It seems unlikely a Republican-controlled Legislature would overturn the ban. Gilbert and others are advocating to at least end criminal and civil penalties for doctors. Though no doctor has been prosecuted for violating the ban, the mere threat of criminal charges continues to obstruct care, she said.

In 2023, an amendment was passed that permitted physicians to intervene when patients are diagnosed with PPROM. But it is written in such a way that still exposes physicians to prosecution; it allows them to offer an “affirmative defense,” like arguing self-defense when charged with murder.

“Anything that can reduce those severe penalties that have really chilled physicians in Texas would be helpful,” Gilbert said. “I think it will mean that we save patients’ lives.”

Rep. Mihaela Plesa, a Democrat from outside Dallas who filed a bill to create new health exceptions, said that ProPublica’s latest findings were “infuriating.”

She is urging Republicans to bring the bills to a hearing for debate and discussion.

Last session, there were no public hearings, even as women have sued the state after being denied treatment for their pregnancy complications. This year, though some Republicans appeared open to change, others have gone a different direction.

One recently filed a bill that would allow the state to charge women who get an abortion with homicide, for which they could face the death penalty.

Shop our Store

Headlines

Editor's Blog

Trending

World